

EBOLA FEARS GROW IN KENYA AS 65 YEAR OLD WOMAN BECOMES THIRD CONFIRMED CASE, BUT HEALTH OFFICIALS INSIST VIRUS HAS NOT SPREAD INTO COMMUNITY
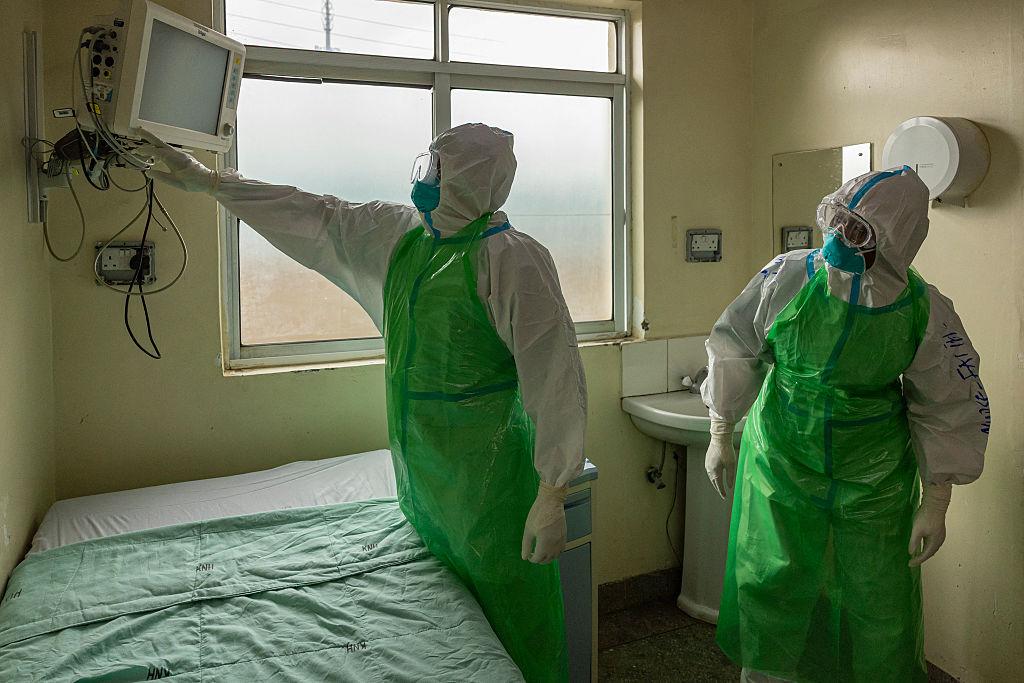
Kenya has confirmed its third case of Bundibugyo Ebola after a 65 year old woman who had been in quarantine since October 6 tested positive. She is a close relative and primary contact of the country’s first two patients and developed fever, sore throat and general weakness while already under monitoring. Officials say 127 of 130 identified contacts have been traced and there is currently no evidence of community transmission. Kenya’s first patient, who had travelled from the Democratic Republic of Congo through Uganda, died in Nairobi on October 5, while the second confirmed patient remains stable.
Kenya has confirmed a third case of Ebola after a 65 year old woman who was already being monitored in quarantine tested positive for the Bundibugyo strain of the deadly virus, deepening concerns over the movement of the disease beyond the Democratic Republic of Congo while Kenyan health authorities insist there is currently no evidence that Ebola is spreading freely within the wider community. The latest patient is a close relative and primary contact of the first two people diagnosed in Kenya, making all three confirmed infections part of the same known transmission chain rather than separate unexplained outbreaks. According to the Ministry of Health, the woman had been under quarantine since October 6 because of her direct connection to the original imported case. She later developed fever, a sore throat and general weakness, prompting health officials to immediately isolate her and collect samples for testing. The results confirmed Ebola, but officials said the fact that she was already under surveillance meant she could be diagnosed quickly and placed under supportive medical care without moving freely through the community after becoming symptomatic.
The confirmation brings Kenya’s total number of known Ebola infections to three, including the country’s first patient, a Kenyan man who had been living in the Democratic Republic of Congo and died in Nairobi on October 5. The second case, confirmed days later, involved a 39 year old man who was also a close family member of the first patient and had similarly been placed in quarantine before developing symptoms. Health authorities say that patient remains stable. The third patient’s infection therefore fits the pattern public health officials hoped to identify when they began tracing relatives, health workers, airline passengers and other people who may have come into contact with the first man. Rather than discovering the virus through an unexplained illness elsewhere in Nairobi or another part of the country, the newest case emerged among people already identified as being at risk.
That distinction is central to the government’s repeated assurance that Kenya has not yet recorded community transmission. Community transmission would indicate infections appearing among people whose exposure cannot easily be traced to known patients, making containment significantly more difficult. For now, the Ministry of Health says all confirmed Kenyan cases remain epidemiologically linked to the first imported case, giving response teams a clearer picture of where transmission occurred and who else may potentially have been exposed. Officials nevertheless remain cautious because Ebola can have an incubation period of up to 21 days, meaning contacts who currently appear healthy may still require continued monitoring until they complete the full observation period.
The Ministry of Health said 130 contacts connected to the first confirmed patient had been identified, with 127 successfully traced and placed under monitoring or quarantine. Authorities are still attempting to locate the remaining three. The high proportion already traced is being presented as evidence that contact tracing is functioning, but even a small number of unaccounted for contacts can remain a serious concern in an Ebola response because an infected person who becomes symptomatic outside quarantine could expose additional people before authorities intervene. Public health officials are therefore continuing daily monitoring of those contacts while reinforcing surveillance at health facilities and major entry points.
Kenya’s first case exposed significant weaknesses in the country’s border and airport screening system because the infected man managed to travel through several countries and eventually enter Nairobi before his illness was confirmed as Ebola. The patient had been living in the Democratic Republic of Congo, where a major Bundibugyo Ebola outbreak has been spreading since May. He became ill while in Congo and later travelled by road through Uganda before eventually flying to Nairobi. By the time he reached Kenya, he was already showing symptoms associated with the disease. Relatives took him to hospital shortly after his arrival, and he later died on October 5. Laboratory testing confirmed Ebola, giving Kenya its first recorded case during the current regional outbreak.
The journey immediately raised uncomfortable questions about how an infected traveller was able to cross borders and move through major transport systems during a period when East African governments were already on alert because of the outbreak in Congo. Kenya had strengthened screening at border posts and airports months before the first domestic case appeared. Health authorities had also activated emergency response structures, increased laboratory preparedness, trained health workers and identified isolation facilities. Yet the first patient still reached Nairobi, demonstrating that screening systems cannot guarantee that every infected traveller will be detected, particularly when symptoms resemble more common illnesses or when travellers do not fully disclose where they have been and whether they have been exposed to Ebola.
The Bundibugyo strain involved in the Kenyan cases is especially concerning because there is currently no licensed vaccine specifically approved for it. Ebola vaccines have played an important role in responding to outbreaks involving the Zaire strain, but the protection provided by those vaccines does not automatically extend to Bundibugyo virus. Researchers are studying potential vaccines and some candidates have reached early stages of human testing, but health authorities currently depend heavily on traditional outbreak control measures. Those measures include rapid diagnosis, isolation of patients, rigorous infection prevention, contact tracing, safe handling of bodies and public cooperation.
Early diagnosis can significantly improve a patient’s chances because supportive treatment can begin before severe complications develop. Ebola treatment includes carefully managing fluids and electrolytes, maintaining oxygen and blood pressure, treating other infections where necessary and responding rapidly to complications. There is no approved Bundibugyo specific antiviral cure. The ministry has therefore emphasised that the 65 year old patient was identified early because she was already quarantined. Health officials say that early diagnosis improves her prospects compared with a situation in which she might have remained untreated until the disease had progressed significantly.
The virus spreads primarily through direct contact with the blood or other bodily fluids of an infected person, particularly after symptoms have begun. It is not transmitted in the same way as common airborne respiratory infections. That makes rapid isolation and contact tracing extremely important because health officials can substantially reduce transmission by identifying and monitoring people who have had close contact with a patient. Healthcare workers and relatives providing direct care are among those at greatest risk without appropriate protective measures.
The current Kenyan infections are linked to an enormous outbreak in the Democratic Republic of Congo that has become one of the most serious Ebola emergencies ever recorded. Congo has reported more than 9,000 confirmed infections and over 4,300 deaths since the Bundibugyo outbreak was detected in May. The epidemic has spread across multiple provinces, with infections recently identified in another province close to the Central African Republic. The outbreak has now become the second largest Ebola epidemic globally by recorded case numbers, surpassed only by the devastating 2014 to 2016 West African epidemic.
The scale of the Congo crisis has made cross border transmission increasingly difficult to prevent. The movement of traders, families, humanitarian workers and other travellers between neighbouring countries means a virus does not necessarily remain contained within national borders, particularly when communities on opposite sides of a border maintain close economic and social relationships. Uganda recorded cases connected to the same regional outbreak before later being declared Ebola free in August. Kenya’s imported case demonstrates that even countries without sustained domestic transmission remain vulnerable while a major outbreak continues elsewhere in the region.
The latest Kenyan case is therefore both worrying and, from an outbreak control perspective, different from an unexplained infection appearing in someone with no known connection to previous patients. The 65 year old woman was already classified as a primary contact, had been quarantined for days and was being monitored for symptoms. When those symptoms appeared, authorities did not have to search for her after she had spent days interacting with members of the public. She was already within the health surveillance system. That is precisely the purpose of quarantine during an Ebola outbreak.
The second confirmed patient followed a similar pattern. He was a 39 year old close relative of the first patient and had also been identified as a contact before becoming ill. Kenyan health authorities said he developed symptoms while already under monitoring and was immediately isolated and tested. His infection was subsequently confirmed. The government has used both cases to argue that its containment measures are functioning because secondary infections are being detected among people known to have been exposed rather than emerging unexpectedly in the general population.
That reassurance does not mean the danger has passed. Ebola response teams must continue monitoring every identified contact through the full incubation period and investigate every suspicious illness quickly. Hospitals must also remain alert because people with fever, weakness, vomiting or other symptoms may initially arrive at ordinary healthcare facilities rather than designated Ebola centres. Infection control failures inside hospitals have historically been responsible for significant transmission during Ebola outbreaks, particularly when healthcare workers treat infected patients before realising what disease they are dealing with.
Kenya has been preparing for this possibility for months. The Ministry of Health had previously activated emergency response structures and increased surveillance at border crossings and airports because of the expanding regional epidemic. Officials strengthened screening procedures, placed isolation centres on standby, trained frontline healthcare workers, distributed protective equipment and improved laboratory testing capacity. Rapid response teams were also deployed around the country, with high risk counties receiving additional attention because of their transport links and proximity to borders.
Jomo Kenyatta International Airport has become a particular focus because of the first patient’s journey. The airport is East Africa’s largest aviation hub and receives passengers from across the continent and beyond. Health authorities have increased screening of travellers arriving from high risk countries, although the first case demonstrated the practical limits of entry screening. A traveller can pass through a checkpoint before symptoms become obvious, or symptoms may not be recognised if they resemble malaria, influenza or another common illness.
The government has consequently urged travellers to disclose accurate information about their recent movements and possible exposure to infected people. Public health experts have repeatedly warned that hiding travel history during an Ebola outbreak can put relatives, healthcare workers and entire communities at risk. Rapid recognition depends not only on technology or temperature screening but also on truthful information from people seeking treatment.
The country’s response is being supported by the World Health Organization and other international partners. WHO confirmed that Kenya’s second and third cases were both close relatives of the initial patient and that both were already in quarantine when they became ill. The organisation has been working with national authorities on surveillance, infection prevention, contact tracing, laboratory services and clinical management. The third case was described as an example of why intensive monitoring of known contacts remains one of the most important tools available during an Ebola outbreak.
Public concern remains understandable because Ebola has one of the most feared reputations of any infectious disease. Severe cases can involve vomiting, diarrhoea, organ failure and internal or external bleeding, although bleeding does not occur in every patient. The disease can be fatal, especially when treatment is delayed. At the same time, public health authorities have urged Kenyans not to panic or stigmatise people who have been quarantined or treated for the disease. Quarantine does not mean a person has Ebola. It means health authorities believe there is enough possibility of exposure to justify monitoring until the incubation period has passed.
Stigma can actively undermine outbreak control because people who fear being rejected by communities may hide symptoms or refuse to cooperate with contact tracers. Previous Ebola outbreaks have demonstrated that community trust can be as important as medical infrastructure. Health teams need families to report illness, communities to accept safe burial practices and contacts to remain available for monitoring. Rumours that health authorities are secretly spreading the disease or hiding information can quickly weaken cooperation.
Kenyan officials have therefore repeatedly emphasised transparency and regular public communication. The ministry says the public risk remains low because the confirmed cases are connected to one known chain of transmission and the majority of contacts have already been identified. The discovery of the third case does not automatically prove that containment efforts have failed. In fact, detecting a known contact while that person is already isolated is one of the outcomes public health teams prepare for when monitoring an exposure network.
The true test will be whether cases begin appearing outside that network. If additional infections are confirmed among people with no identifiable link to the original patient or his known contacts, officials would face a much more difficult situation because that could indicate undetected chains of transmission. So far, the ministry says it has found no such evidence.
The remaining three untraced contacts are therefore receiving considerable attention. Authorities have not publicly disclosed detailed information about their identities because patient and contact confidentiality must be protected, but health teams are continuing efforts to locate them. Regional authorities in countries connected to the first patient’s travel history are also sharing information about possible contacts.
Kenya’s outbreak comes at a particularly difficult moment because Congo’s epidemic continues expanding. The number of infections there has passed 9,000, with more than 4,300 people reported dead. Cases have now been detected in several provinces, while conflict, displacement and weak health infrastructure are complicating containment efforts. In some areas, healthcare workers have struggled to persuade people to seek treatment early, and a significant number of deaths have occurred outside specialised Ebola treatment centres.
The absence of a licensed Bundibugyo vaccine makes regional containment even more dependent on surveillance and behavioural measures. During outbreaks involving vaccine preventable Ebola strains, health teams can sometimes vaccinate contacts and contacts of contacts to build a protective ring around confirmed cases. That tool is not currently available in the same established form against Bundibugyo, placing even greater importance on finding exposed people quickly.
The regional dimension also means Kenya cannot eliminate its risk simply by controlling the three cases already identified. As long as substantial transmission continues in Congo, there remains a possibility that another infected traveller could enter Kenya independently of the current family cluster. Authorities must therefore manage two risks simultaneously: preventing further transmission from the existing Kenyan cases and detecting any additional imported cases arriving through airports, border crossings or informal routes.
This dual challenge explains why Kenya’s response has expanded far beyond the household connected to the first patient. Screening measures remain in place at major entry points, hospitals have been told to maintain heightened vigilance and laboratories are prepared to rapidly test suspected cases. Health workers have also been reminded to use appropriate infection prevention measures when dealing with patients whose symptoms and travel histories could indicate Ebola.
For ordinary Kenyans, officials are recommending vigilance rather than panic. Members of the public are being advised to avoid direct contact with the bodily fluids of anyone suspected of having Ebola, report suspicious symptoms promptly and cooperate with public health authorities. People who have not had contact with a confirmed case or travelled through affected areas do not face the same level of risk as those within known exposure networks.
The latest diagnosis therefore presents Kenya with a serious but still potentially containable public health challenge. Three confirmed infections, one death and more than one hundred monitored contacts are significant developments, particularly for a country that had not previously been at the centre of the current outbreak. Yet the fact that both secondary cases were already in quarantine when symptoms appeared gives health authorities an important advantage.
Much will depend on the coming days. If the remaining contacts complete their monitoring periods without illness and no unexplained cases emerge, officials will have stronger evidence that transmission has been contained within the known family cluster. If additional contacts test positive while already quarantined, the number of confirmed cases may rise without necessarily proving widespread community transmission. What health officials fear most is the appearance of infections outside the known chain.
For now, the government’s position remains unchanged. Kenya has three confirmed Bundibugyo Ebola cases, all linked to the first imported patient. The latest patient is receiving supportive care after being identified early. The second patient remains stable. The first patient died on October 5 after arriving from the Democratic Republic of Congo through Uganda. Most identified contacts are under surveillance, three remain to be traced and authorities say they have found no evidence that the virus is circulating freely within Kenyan communities.
The confirmation of a third case inevitably increases anxiety, but it also demonstrates why the original contacts were quarantined in the first place. Kenya is now in a race against the incubation clock, watching each exposed person for signs of illness while strengthening surveillance against another imported infection. Whether the country contains the outbreak at three cases or records additional patients will depend on how effectively that system performs over the coming days and weeks.



